
can a torn tendon heal on its own
Can a Torn Tendon Heal on Its Own? How to Choose the Right Next Step
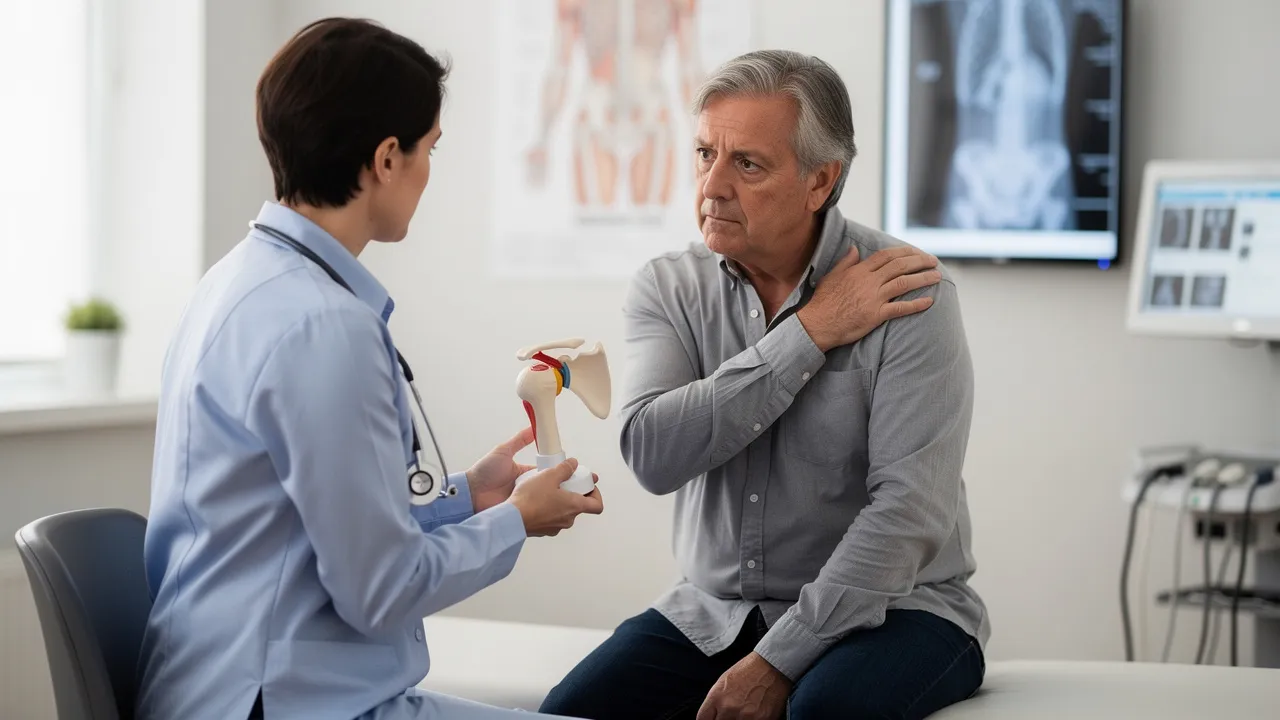
Healing is not the same as adequate recovery
The more useful question is not simply whether tissue can repair itself. It is whether the injury pattern and recovery course support the level of function you need.
An acute tendon injury may heal with an acceptable recovery of function, yet the quality of biological or surgical repair rarely returns fully to pre-injury levels. That distinction matters if you are trying to decide whether continued observation is reasonable. A reduction in pain can coexist with incomplete structural recovery, while persistent weakness or loss of function can signal that the situation deserves closer assessment.
Your next step depends on more than the word “tear.” Consider four parts of the picture together: how the problem began, what function changed, whether the pattern is settling or persisting, and how much uncertainty remains about the actual tendon damage. This approach avoids both false reassurance and the assumption that every suspected tear requires an operation.
Recovery has a structural side and a practical side. Structural healing concerns the tendon tissue itself. Practical recovery concerns whether you can use the affected shoulder, elbow, ankle, hand, or other body region for the tasks that matter to you. Those two measures can move at different speeds, so less pain is useful information but not proof that the tendon has returned to its prior capacity.
The answer also changes with the type of damage. A sudden injury to previously healthy tissue is not the same starting point as a tear developing in tissue affected by chronic degeneration. A partial tear is not the same structural problem as a complete rupture. General tendon-healing information can frame the decision, but it cannot identify your tear severity from a symptom description.
First distinguish irritation, partial tearing, and rupture
Tendon irritation, a partial tear, and a major rupture describe different levels of concern, but pain alone cannot reliably place your symptoms into one category. Irritation or tendinopathy describes a problem involving tendon symptoms and tissue change; it does not, by itself, establish that fibers are torn. A partial tear means that some tendon tissue has been disrupted. A full-thickness tear or rupture represents more extensive separation of the tendon structure.
Tendon damage may be acute or chronic. Acute damage involves sudden disruption of previously healthy tissue, such as an injury caused by a distinct event. Chronic damage involves degenerative tissue changes that accumulate over time. These categories can overlap in real situations: a tendon with prior tissue change may become vulnerable to a new injury, while a sudden injury can create a separate problem in previously healthy tissue.
A useful general map is:
- Irritation or tendinopathy: symptoms and tendon changes that do not automatically prove a tear.
- Partial tearing: disruption of part of the tendon, sometimes in tissue already affected by overload or tendinopathic change.
- Full-thickness tearing or rupture: more extensive disruption that can alter the tendon’s continuity and function.
These labels describe categories rather than a diagnosis for your symptoms. The same body region can produce pain from more than one tendon problem, and the practical significance of a finding depends on the examination and the function that has changed.
Evidence concerning partial Achilles tendon tears associates many of them with tendon overload and tendinopathic tissue changes, although the precise process is not fully understood. That finding should not be transferred mechanically to every shoulder, elbow, or other tendon problem. It does show why a painful tendon can have a longer history than the moment when symptoms became noticeable.
A partial tendon tear can extend to a full-thickness tear, and imaging may have difficulty distinguishing a partial tear from tendinosis. That possibility does not mean progression is happening in your case. It means that continued symptoms, changed function, or uncertainty about the injury pattern deserve a more specific conversation instead of a conclusion based on pain intensity alone.
When you describe the problem, separate what you know from what you suspect. You may know that pain began after a particular movement, that lifting has become difficult, or that symptoms have persisted. You may suspect a tear because of the pain or a prior scan. Keeping those statements separate helps prevent a symptom from becoming an unconfirmed diagnosis.

What can affect whether healing is adequate
The mechanism and condition of the tendon can influence how adequate healing will be. A sudden disruption of previously healthy tissue is a different starting point from a tear occurring in tissue that has already experienced chronic degenerative change. In partial Achilles tears, repeated mechanical overload and tendinopathic tissue changes are commonly associated with the injury pattern, although the exact pathogenesis remains uncertain.
Several tissue conditions can change the healing environment:
- Damage to a tendon’s blood supply can hinder healing.
- Loss of tendon integrity can contribute to adhesions and altered motion.
- Surrounding inflammation can be associated with adhesion formation.
- Adhesions can reduce the affected joint’s range of motion.
- A partial defect can extend into a more extensive tear.
These are general biological factors, not a way to predict your outcome from symptoms. The same amount of pain can occur in different tendon conditions, and the same imaging finding can have different practical implications depending on function and the rest of the examination.
Acute and chronic damage can create different questions. After an acute event, the concern may be whether the tendon has been disrupted and how that disruption affects use of the limb. With chronic symptoms, the concern may include accumulated tissue change, altered movement, or a problem that has not settled as expected. Damage to the tendon’s blood supply can hinder healing, so the tissue environment matters alongside the original mechanism.
Adhesions provide one example of why healing and function are related but not identical. Adhesion formation may be associated with impaired blood supply, loss of tendon integrity, and surrounding inflammation. When adhesions reduce joint range of motion, the practical effect may be a restriction in movement even if pain has changed. A report of improving pain therefore needs to be considered with your actual movement and use of the affected joint.
Adequate recovery therefore has two dimensions: what happens within the tendon and what you can do with the affected limb. A tendon may repair with an acceptable return of function without returning completely to its pre-injury tissue quality. Conversely, a persistent restriction in joint motion may matter even if pain has become less intense. Track the function you need rather than treating symptom reduction as proof that the tissue is fully restored.
For your decision, ask whether the overall pattern is moving toward the function you need. If movement remains restricted, a task remains difficult, or the problem continues without a clear explanation, the biological factors above make an assessment more useful than guessing from pain alone. They explain why two people with similar symptoms may not have the same next step.
Why symptoms cannot establish tear severity
Symptoms cannot establish whether a tendon is irritated, partially torn, or fully disrupted. Weakness, reduced motion, or difficulty with a specific task can add useful context, but those features still do not identify tear severity on their own.
The study population and clinical question matter. Findings from shoulder imaging cannot be treated as a universal ranking of tests for every tendon in every situation.
The practical point is simple: an image should answer a clinical question rather than replace the examination. If your symptoms and function leave the injury pattern uncertain, an assessment can help determine whether imaging is relevant, which type may address the question, and how the result fits with what you can actually do.
An imaging report also needs context. When you discuss a scan, ask what structure was examined, whether the finding is partial or full thickness, whether the finding could represent tendinosis instead, and whether it explains the function that has changed. These questions keep an abnormal image from becoming an automatic explanation for every symptom.
A normal or inconclusive clinical impression does not answer every tendon question either. For some injuries, examination findings may be inconsistent or may change after the problem has been present for a longer period. When the history, examination, and function do not line up, the remaining uncertainty is itself a reason to discuss the next assessment step.
Use mechanism, function, persistence, and warning signs to set the pace
The pace of your next step should follow the uncertainty and the change in function, not a fixed timetable. A distinct injury event, a noticeable loss of a movement you previously performed, symptoms that remain unresolved, or a pattern that does not fit the initial explanation all make indefinite observation less useful. These features do not diagnose a tear, but they give you a reason to seek a more specific assessment.
Achilles injuries illustrate why timing and examination findings matter. Inconsistent findings on examination may warrant MRI. When a tear is subacute or chronic, with the injury occurring more than four weeks before assessment, scar tissue can alter examination findings and make the clinical picture more difficult to interpret.
Use this decision screen to organize the next conversation:
- Mechanism: Was there a sudden event, or did symptoms build after repeated loading?
- Function: What movement, lift, push, pull, or step has changed?
- Persistence: Is the problem settling, or has it remained unresolved over time?
- Uncertainty: Do the symptoms and function point clearly in one direction, or could several tendon conditions explain them?
- Concerning change: Has the pattern become harder to interpret because the problem has continued or function has changed?
If the pattern is uncertain or function remains meaningfully altered, arrange an assessment rather than relying on symptoms to determine tear severity.
The decision can be organized into three broad branches:
- The pattern is settling: Continue the general plan already provided by your clinician and keep the changes in function under review. Reassessment remains appropriate if the course stops settling.
- The pattern is persistent or unclear: Arrange a professional assessment so the history, function, examination, and possible imaging can be considered together.
- The pattern followed a distinct injury and function changed substantially: Seek timely clinical assessment rather than assuming that pain improvement proves adequate healing.
These branches help set the pace without assigning a diagnosis or an individualized activity plan.
A general decision guide cannot determine whether your injury needs urgent attention from a description alone. A sudden suspected disruption, an inconsistent examination, or a longer-standing problem with altered findings deserves timely clinical discussion. The purpose of that discussion is to establish what is known, what remains uncertain, and whether monitoring is still a reasonable path.
Whether you are managing work, training, or daily activity in Palo Alto, San Francisco, or elsewhere in the Bay Area, the useful question is the same: has the tendon problem settled enough for the function you need, or does the remaining uncertainty justify assessment? Local setting does not replace that clinical question.
An evaluation can clarify what symptoms leave uncertain
An evaluation connects your history, functional changes, physical findings, and any imaging into one decision. It does not turn every painful tendon into a confirmed tear. Instead, it helps clarify whether the suspected structure matches the symptom pattern and whether the next question concerns observation, further imaging, rehabilitation, or a discussion of procedural options.
An imaging finding is only one part of the question. The practical issue is whether it explains the functional problem and changes the available paths.
The appropriate process also varies by tendon and timing. For an Achilles injury, inconsistent examination findings may warrant MRI, while scar tissue in a subacute or chronic tear occurring more than four weeks before evaluation can alter the examination. Your evaluation should therefore answer a specific question instead of treating imaging as an automatic first or final step.
Before an evaluation, organize the information that will shape the question:
- The date or circumstances when symptoms began.
- The movement or load that first caused trouble.
- The function you could perform before the problem and what changed afterward.
- Whether symptoms have improved, remained stable, or worsened.
- Any prior imaging and the treatment or injection history connected to the tendon.
This preparation does not diagnose the injury. It makes it easier to connect the scan, examination, and functional problem.
A useful evaluation should leave you with a clearer account of the uncertainty. You may learn that the clinical findings support monitoring, that imaging would answer a more specific question, or that the original label does not explain the functional change. The value is not in ordering a test automatically; it is in matching the assessment to the decision you need to make.
Non-operative care is a monitored path, not a guarantee
Non-operative care is not one treatment and it is not a promise that a tendon will heal adequately without surgery. It is a monitored path whose suitability depends on the actual injury pattern, your function, the clinical findings, and how the problem changes over time. A plan can be reconsidered when the working explanation no longer fits.
Depending on the condition being assessed, non-surgical discussions may include:
- Observation with planned reassessment when the overall pattern is settling and no unresolved feature changes the decision.
- Clinician-directed rehabilitation and functional follow-up, with the response used to reassess the working diagnosis.
- Procedures intended to address symptoms or tissue healing, such as shockwave therapy in selected tendinopathy discussions.
- Further examination or imaging when symptoms, function, or the initial findings leave the tendon problem uncertain.
These categories describe possible topics for assessment, not individualized instructions or a prediction of benefit.
Shockwave therapy is described as a treatment intended to relieve pain and help injured tissue heal. That wording describes the purpose of the treatment, not a guaranteed result for a particular tendon or tear. The same source notes that repeated steroid injections for tendinopathy can weaken a tendon and increase tearing risk over time, so the history of prior treatment belongs in the discussion.
Monitoring has to include a reason to reassess. If function remains changed, symptoms persist, or the clinical findings become inconsistent with the original explanation, continued observation without review leaves the central question unanswered: whether the tendon is recovering adequately for the demands you place on it.
Non-surgical treatment categories are not interchangeable. Observation asks whether the problem is settling with follow-up. Rehabilitation focuses on function under clinical direction. Shockwave therapy is described as an intended treatment for pain and injured tissue healing in tendinopathy discussions. Imaging addresses a diagnostic question. Each belongs at a different point in the conversation, and none can be selected responsibly from the word “tendon” alone.
Prior injections also change the information that should be considered. For tendinopathy, repeated steroid injections can weaken a tendon and increase tearing risk over time. That does not determine what happened in your case, but it gives the treatment history a direct place in the evaluation. Include the type and timing of previous treatment when you discuss persistent tendon symptoms.
The boundary is straightforward: general information can help you compare questions, but it cannot tell you whether a specific tendon will heal, whether a procedure will help, or whether surgery can be avoided. Those conclusions depend on the injury pattern, examination, function, and follow-up.
Surgery and non-surgical care involve different trade-offs
Surgery is not automatically necessary, and avoiding surgery is not automatically the better choice. The comparison concerns acute Achilles tendon rupture, so it should not be transferred directly to a rotator cuff, elbow, or other tendon problem. It does show why the decision requires more than a preference for or against an operation.
| Decision factor in acute Achilles tendon rupture | Operative treatment | Non-operative treatment |
|---|---|---|
| Re-rupture in the systematic review | 2.3% | 3.9% |
| Complications in the systematic review | 4.9% | 1.6% |
| Patient-reported outcomes and physical performance in randomized trials | Similar outcomes were reported between approaches | Similar outcomes were reported between approaches |
The figures describe groups of people with acute Achilles ruptures, not your personal probability. The review found fewer re-ruptures after operative treatment but more complications, while randomized trials reported similar patient-reported outcomes and physical performance between approaches. The evidence also describes infection and nerve injury among surgical risks and a higher re-rupture risk with non-operative treatment.
The comparison also has boundaries. It concerns acute Achilles tendon rupture, not every tendon injury, and the studies used different treatment and rehabilitation protocols. A result from this group cannot establish what should happen with shoulder pain, a suspected rotator cuff tear, tennis elbow, or another condition. It can, however, show why both benefit and complication trade-offs belong in the discussion.
When surgery is being discussed, make the comparison specific:
- What tendon and tear pattern are being considered?
- What function are you trying to regain?
- What does non-operative care involve, and how will progress be assessed?
- What re-rupture or persistence concerns apply to this injury?
- What complications, including infection or nerve injury, apply to the proposed operation?
These questions keep the decision tied to your injury rather than to a general belief that one treatment category is always preferable.
Use the comparison to make the discussion more specific: identify the tendon involved, the injury pattern, the functional demand you need to meet, and the trade-offs attached to each path. Do not use acute Achilles evidence as a guarantee for a shoulder or elbow tear. For those injuries, the next decision depends on an assessment that fits the body region and the suspected damage.

What a focused evaluation can establish
A focused discussion can also separate three different decisions: whether the tendon problem needs more assessment, whether a non-operative path is reasonable to discuss, and whether a particular treatment fits the finding. Those decisions should not be collapsed into one promise. A scan may clarify structure, while the examination and your function help determine what the finding means for the next step.
An evaluation can clarify whether a non-operative approach is reasonable to discuss, but it cannot promise healing, eliminate the possibility of surgery, or guarantee a particular recovery. Its value lies in replacing an uncertain label with a more specific understanding of the tendon problem and the available next conversation.
Choose the next conversation based on the remaining uncertainty
The decision to monitor or seek further assessment should follow the injury pattern, functional change, persistence, and remaining uncertainty. Monitoring makes more sense when the overall pattern is settling and no unresolved feature changes the decision. Timely assessment makes more sense when a sudden suspected disruption, altered function, persistent symptoms, inconsistent findings, or uncertainty about severity continues to shape the problem.
Bring the decision back to the question your symptoms cannot answer alone: what is damaged, how much function has changed, and what evidence would justify continuing to monitor or changing direction. A qualified professional should decide individual suitability for a treatment or activity plan.
Questions to ask before deciding whether to wait or seek an evaluation
How long does it take for a torn tendon to heal without surgery?
There is no single healing time that applies to every tendon injury. The course depends on the tendon involved, whether the damage is irritation, partial tearing, or rupture, whether the tissue had prior degeneration, and whether function is improving. Pain reduction alone does not confirm adequate structural recovery. Persistent symptoms, changed function, or uncertainty about tear severity are reasons to arrange an assessment rather than rely on a fixed timeline.
How do you know whether a tendon injury needs professional assessment?
Arrange timely assessment when symptoms follow a distinct injury, function has noticeably changed, symptoms remain unresolved, or the examination and symptoms do not fit together. These features do not prove a tear, but they make indefinite observation less useful. Assessment can connect the history, functional changes, examination, and—when appropriate—ultrasound or other imaging.
Next step
Have a question for RegenCore?
Concierge regenerative & orthobiologic orthopedics in San Francisco and Palo Alto. Research-backed, non-surgical treatment — PRP, bone marrow concentrate (BMAC), stem cell therapy, shockwave, EMTT and spinal disc care — to help the body heal itself.
Get in touch