
mechanical pain
What Is Mechanical Pain? Understanding Movement-Related Musculoskeletal Symptoms
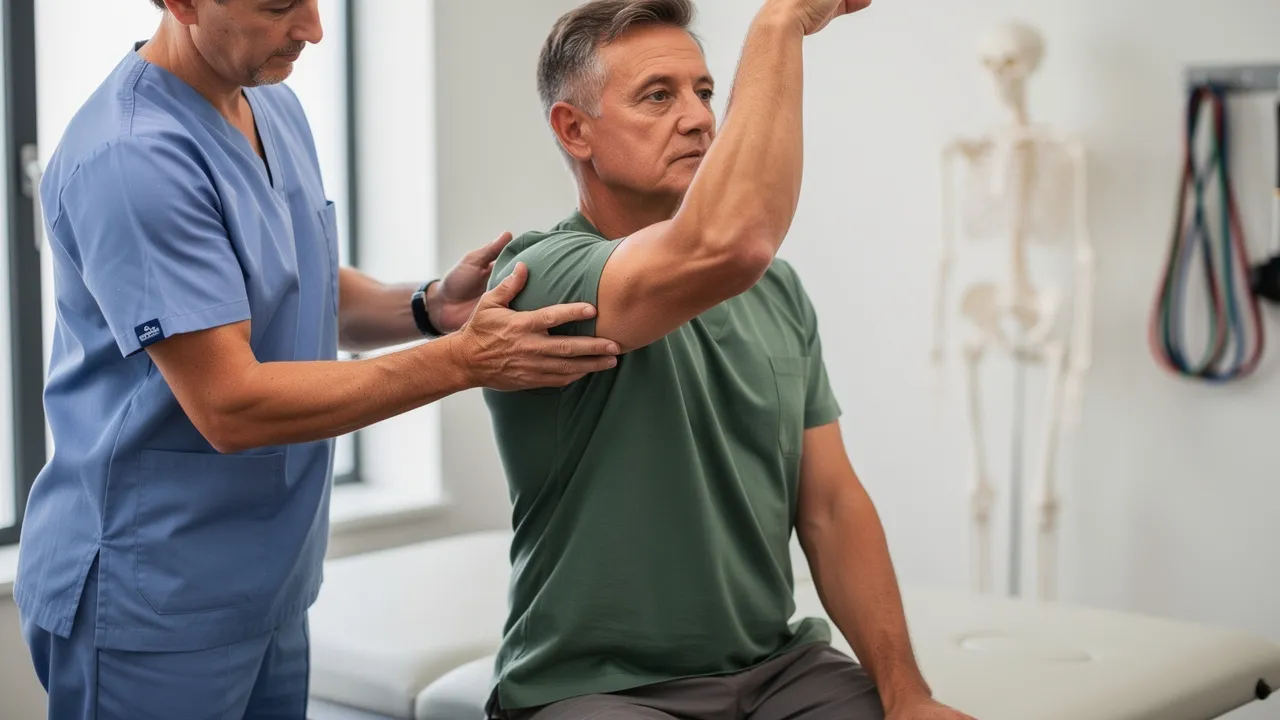
Mechanical Pain Describes a Pattern, Not a Diagnosis
Mechanical pain describes a pattern in which symptoms appear to change with movement, physical loading, position, posture, or stress placed on the musculoskeletal system. The term can help you describe what your pain does, but it does not identify the injured or irritated structure by itself.
You might notice discomfort when you reach overhead, lift an object, turn your neck, sit in one position, walk, climb, or return to sport. You might also notice that a change in position alters the intensity or location of the symptom. Those observations are useful information to bring to an evaluation. They are not a self-diagnostic test.
This distinction matters because several tissues can produce pain in the same area. Shoulder symptoms, for example, may involve the shoulder joint, a tendon, the bursa, the neck, or another nearby structure. A similar movement trigger can occur with more than one condition, and the absence of a trigger does not rule out a musculoskeletal source.
Shoulder pain is often nonspecific, so its cause cannot be identified reliably from symptoms alone; careful history-taking and physical examination are important. That principle applies whether your symptoms began after a clear injury, developed gradually, or have lingered after rest or a previous treatment.
The practical takeaway is simple: describe the pattern without turning it into a diagnosis. Note what changes the symptom, how long the change lasts, what activities have become difficult, and whether the problem is stable, worsening, or unclear. Then use that information to guide a professional conversation.
How Movement, Loading, and Posture Can Shape Symptoms
Movement, loading, and posture give you three useful ways to describe a symptom pattern. They also have limits. None of them can identify a specific tissue without a clinical assessment.
- Movement: Reaching, rotating, bending, pushing, or pulling may reproduce pain because the action changes the position or demand placed on the affected region. Record the movement that brings on the symptom rather than assuming that the movement caused a particular injury.
- Loading: Lifting, carrying, running, serving, throwing, or repeated overhead work can increase demand on muscles, tendons, joints, and surrounding tissues. A flare after activity may show that the area is sensitive to that demand, but it does not tell you which structure is responsible.
- Posture and position: Sitting, sleeping, working at a desk, driving, or holding an arm in one position may change symptoms. Position can be a useful part of your history, especially if you are active around Palo Alto or the wider Bay Area and are trying to balance work, commuting, training, and daily tasks.
Think of these observations as clues for a conversation. They are not pass-or-fail tests that prove a diagnosis.
Shoulder bursitis illustrates why activity patterns need context. It can develop when the subacromial bursa becomes inflamed, often after repetitive overhead activity, and symptoms may worsen with overhead use or while sleeping. If reaching or sleeping changes your shoulder pain, that description may help a clinician ask better questions; it does not establish bursitis.
The same caution applies to pain that follows exercise, work, or sport. A symptom that appears during a particular task may reflect the task’s demand, the position of the joint, a nearby structure, or a source outside the painful area. Stop short of assigning a cause from the trigger alone.
A short symptom record can make these patterns easier to explain. Write down the activity or position involved, whether the symptom began during or after it, how long the change lasted, and what function was affected. Include both aggravating and easing factors without treating either as proof of a diagnosis.
For example, “pain after repeated overhead work” gives a different starting point for questions than “shoulder pain.” The added detail does not name the condition, but it helps connect your experience to the history and examination.

Common Mechanical Pain Examples in the Shoulder and Back
Shoulder symptoms often change with reaching, lifting, sleeping, or other use of the arm. Several conditions can produce that kind of pattern.
- Shoulder bursitis: Inflammation of the subacromial bursa can follow repetitive overhead activity. Pain may worsen with overhead use or while sleeping.
- Rotator cuff tendinitis: One clinical overview describes this as the most common cause of shoulder pain and says it can develop gradually from irritation or inflammation of one or more rotator cuff tendons. Symptoms may be noticed when you raise or lower the arm.
- Shoulder impingement: Rotator cuff tendons or the bursa can become pinched between the upper-arm bone and the acromion. This can cause pain, weakness, and difficulty reaching overhead or behind the back.
These examples show why a movement-related pattern can be meaningful without being conclusive. The same activity may aggravate different conditions, and similar conditions may behave differently from person to person.
Mechanical back pain can arise from spinal structures such as bones, ligaments, discs, joints, nerves, and meninges. One review reports that this category accounts for 97% of back-pain cases. The figure refers specifically to mechanical back pain within that review; it does not describe shoulder pain, elbow pain, or every type of pain in the body.
Common causes listed for mechanical back pain include spinal stenosis, herniated discs, zygapophysial joint pain, discogenic pain, vertebral fractures, sacroiliac joint pain, and myofascial pain. The range of possible sources is the key point. Back pain that changes with movement or loading may still require an evaluation to determine what is contributing to it.
If your symptoms involve the elbow, the same reasoning applies even though the specific structures differ. Pain during gripping, throwing, lifting, or repetitive work can describe how the symptom behaves. It cannot, by itself, distinguish among tendon, joint, nerve, or referred sources.
Why Shoulder and Tendon Pain Can Be Difficult to Localize
Shoulder pain can be difficult to localize because the painful area is not always the same as the structure generating the symptom. Shoulder pain may be referred from the neck or arise from problems involving the rotator cuff, scapula, labrum, acromioclavicular joint, biceps tendon, degenerative joint disease, or shoulder dislocation.
That range of possibilities explains why pointing to the sorest spot is not enough. The front, side, or back of your shoulder may hurt, yet the relevant clinical questions may involve your neck, range of motion, strength, injury history, work demands, or sports activity. The location still matters, but it is one part of the history rather than a complete answer.
You can make an evaluation more useful by describing the symptom in concrete terms:
- Where did it begin, and where do you feel it now?
- Which movement, position, or load changes it?
- Did it begin suddenly, gradually, or after a specific event?
- Does weakness, loss of function, or a change in movement accompany the pain?
- Has the pattern remained the same, worsened, or spread?
These questions do not diagnose you. They organize the information a clinician may use to decide which possibilities deserve closer attention.
Mechanical Patterns Compared With Other Pain Mechanisms
A movement-related pattern can overlap with other pain mechanisms. Comparing broad patterns can help you understand why symptom descriptions are useful, while also showing why they cannot replace an examination.
Movement- or load-related pattern: Symptoms may change with a particular movement, position, activity, or physical demand. This pattern can point toward a musculoskeletal question, but it does not identify the tissue, severity, or cause. Use it to describe what happens, not to label the condition.
Nerve-related source: Shoulder pain may be referred from cervical nerve compression, meaning the source can involve the neck rather than the shoulder tissues themselves. A shoulder trigger therefore does not prove that the shoulder is the only area involved. Ask for an assessment when the location, movement pattern, or associated changes are unclear.
Possible nociplastic pattern: Pain hypersensitivity, fatigue, disturbed sleep, cognitive difficulties, and sensitivity to other sensory stimuli may contribute to assessing chronic nociplastic pain. These features are not specific to it, however, so their presence does not establish that mechanism.
The patterns can also overlap. A symptom that changes with movement may coexist with sensitivity, referred pain, or another contributor. For that reason, avoid trying to sort yourself into a category from one symptom, one trigger, or one internet checklist.

What a Clinical Evaluation Is Designed to Determine
A clinical evaluation is designed to connect your symptom history with examination findings and, when appropriate, imaging. The aim is not to treat every painful area as if it had an obvious single cause. Shoulder pain is often nonspecific, so careful history-taking and physical examination help determine which explanations deserve attention.
A useful evaluation may consider:
- The history: how the problem began, what changes it, what activities you need to resume, and whether it is progressing.
- The physical examination: movement, strength, tenderness, and other findings relevant to the painful region and nearby areas.
- The possible source: whether the pattern fits a shoulder structure, the neck, the back, or another musculoskeletal region.
- The need for imaging: whether an image would add information that the history and examination cannot provide.
Imaging has different roles. X-rays can show shoulder-bone injuries, while MRI scans and ultrasound provide better images than X-rays of soft tissues and may help identify injuries to surrounding ligaments and tendons. That does not mean every painful shoulder requires every test. The clinical question should guide the choice.
At RegenCore Method, our evaluations include a thorough history, hands-on orthopedic examination, diagnostic ultrasound, review of prior MRI or X-ray imaging, and a personalized treatment and recovery plan. That process is intended to organize the information needed for a more informed care discussion; it does not turn a symptom pattern into a diagnosis on its own.
You can prepare for an evaluation by bringing prior imaging reports, noting earlier treatments, and writing down the activities or positions that change your symptoms. It also helps to describe what you want to resume, such as work, training, lifting, or sleep without interruption.
During the discussion, ask what working explanations are being considered, which findings support them, what uncertainty remains, and why a proposed care option fits the findings. Those questions keep the conversation tied to your circumstances rather than to a symptom label alone.
When Persistent, Worsening, or Unusual Pain Needs Attention
Persistent pain deserves a closer look when it interferes with sleep, work, training, or ordinary movement, especially if the pattern is worsening or remains unexplained. For mechanical back pain specifically, pain that persists for more than 4 to 6 weeks may warrant further diagnostic testing and imaging. That time frame applies to the cited back-pain guidance; it should not be used as a universal rule for every shoulder or elbow symptom.
Arrange professional evaluation when pain is persistent, worsening, severe, unusual, or unclear. Bring a short record of when it began, what changes it, what function you have lost, and any prior imaging or treatment. Avoid using temporary improvement or a familiar trigger as proof that the cause is harmless.
Serious conditions can sometimes underlie pain. NICE guidance includes cauda equina syndrome, giant cell arteritis, and lung carcinoma among its examples; lung carcinoma may present with severe shoulder pain and Horner’s syndrome. Severe or unusual symptoms that raise concern should receive prompt medical assessment rather than self-treatment based on a mechanical explanation.

How Evaluation Can Guide Non-Surgical Care Options
Non-surgical care should be considered in relation to the suspected source, your examination findings, your goals, and the way the problem affects your function. A movement trigger alone is not enough to choose a treatment. The same symptom may call for different discussions depending on whether the contributing issue involves a tendon, joint, neck, nerve, or another structure.
An evaluation can help clarify:
- which parts of your history need further investigation;
- whether the examination supports a shoulder, elbow, back, neck, or referred source;
- whether imaging may add useful information; and
- which care options are reasonable to discuss for the working clinical impression.
This approach keeps the decision connected to your individual findings rather than to a general label.
A free evaluation is available through RegenCore Method. If you are in Palo Alto or the surrounding Bay Area and want to explore non-surgical care, that evaluation provides a structured starting point for discussing what may be appropriate. It does not promise that a particular treatment will fit your symptoms or produce a particular result.
Before choosing a non-surgical option, make sure you understand the working clinical impression, the goal of the proposed care, and what would prompt a change in the plan. You can also ask how your examination and any imaging relate to the recommendation. The point is not to select care from a symptom description; it is to make the discussion specific enough for an individualized decision.
Choose an Informed Next Step for Ongoing Musculoskeletal Pain
Movement-related symptoms can help you explain your pain, but they cannot tell you exactly what is causing it. If your shoulder, elbow, back, or other musculoskeletal pain persists, worsens, limits activity, or remains unclear, a professional evaluation can help organize the next questions and care options. A qualified professional should decide whether an individual treatment is suitable for you.
That is the appropriate boundary between learning about a symptom pattern and making an individualized care decision.
Questions Readers Commonly Ask About Mechanical Pain
What is considered mechanical pain?
Mechanical pain is a symptom pattern that changes with movement, physical loading, posture, position, or stress on the musculoskeletal system. It describes how pain behaves, not the specific tissue or condition causing it, so it should not be used as a diagnosis by itself.
What are common examples of mechanical pain?
Examples include shoulder pain that changes with reaching or overhead activity, elbow pain during gripping or throwing, and back pain related to movement or loading. Possible sources may include tendons, bursae, joints, discs, muscles, ligaments, nerves, or referred pain from another area. Similar symptoms can come from different causes.
How long can mechanical back pain last before it should be evaluated?
There is no universal timeline for every musculoskeletal problem. For mechanical back pain specifically, pain persisting for more than 4 to 6 weeks may warrant further diagnostic testing or imaging. Evaluation is appropriate sooner when pain is severe, worsening, function-limiting, unusual, or unclear.
When should movement-related pain receive prompt medical attention?
Seek prompt medical assessment for severe or unusual pain, worsening symptoms, significant loss of function, or symptoms that do not fit a straightforward musculoskeletal pattern. Serious conditions can sometimes underlie pain, so a movement-related trigger should not be used to dismiss concerning symptoms.
Does mechanical pain always require an MRI or other imaging?
No. The need for imaging depends on the history, examination findings, and clinical question. X-rays can show shoulder-bone injuries, while MRI and ultrasound can provide more information about soft tissues; a clinician can determine whether imaging is likely to add useful information.
Can symptoms alone distinguish mechanical pain from nerve-related or nociplastic pain?
No. Movement-related symptoms can overlap with nerve-related, nociplastic, or other pain mechanisms. Shoulder pain may be referred from the neck, and features such as pain hypersensitivity, fatigue, or disturbed sleep are not specific to nociplastic pain. History and examination are needed to interpret the overall pattern.
Next step
Have a question for RegenCore?
Concierge regenerative & orthobiologic orthopedics in San Francisco and Palo Alto. Research-backed, non-surgical treatment — PRP, bone marrow concentrate (BMAC), stem cell therapy, shockwave, EMTT and spinal disc care — to help the body heal itself.
Get in touch