
anatomy shoulder tendons
Anatomy of Shoulder Tendons: Locations, Roles, and What Symptoms Can—and Cannot—Tell You
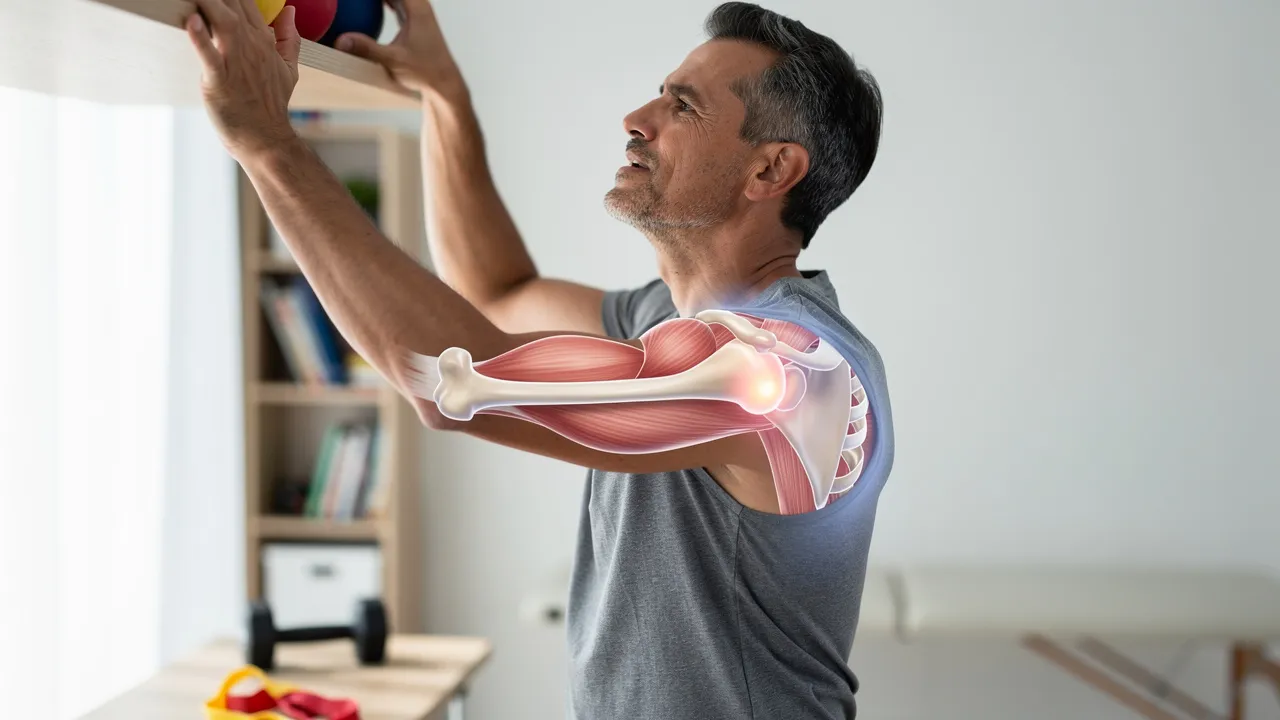
Shoulder tendon anatomy makes more sense as a working system
The shoulder is a working system made up of bones, cartilage, the labrum, ligaments, the capsule, tendons, and muscles. Tendons are only one part of that arrangement. If you feel pain when reaching for a shelf, putting on a jacket, swimming, climbing, or playing a Bay Area weekend sport, the sensation may be coming from a structure that works beside a tendon rather than from the tendon alone.
The main shoulder joint is the glenohumeral joint, a ball-and-socket joint formed by the rounded head of the humerus and the glenoid fossa of the scapula. The humerus is the upper-arm bone, and the scapula is the shoulder blade. This joint gives your arm a wide range of movement, but that freedom depends on several structures working together.
The glenoid fossa is a shallow socket reinforced by muscles, ligaments, and cartilage. The labrum surrounds the socket and extends it while preserving flexibility. That arrangement helps explain why you cannot understand shoulder symptoms by looking at one tendon in isolation: the socket, the soft-tissue supports, and the moving upper-arm bone all participate in how the joint functions.
This does not mean that ordinary shoulder pain indicates instability. It means that shoulder symptoms need to be interpreted in the context of the joint’s full structure rather than assigned to a tendon from location or sensation alone.
Tendons, muscles, and ligaments perform different jobs
Tendons, muscles, and ligaments are different tissues with different connections. Tendons connect rotator cuff muscles to bones and transmit muscle contraction to move the shoulder and upper arm. A muscle contracts; its tendon carries that pull toward the bone. The tendon is therefore a connection between the force-producing muscle and the moving skeleton, not the muscle itself.
Shoulder ligaments connect bones and help stabilize the shoulder and nearby bony structures. A ligament is not a tendon with a different name. A tendon links muscle to bone, while a ligament links bone to bone. The distinction matters because pain near the shoulder can involve several tissues that sit close together and contribute to the same movement.
A useful way to organize the anatomy is to ask three separate questions:
- Which muscle is contracting?
- Which tendon transmits that contraction to the humerus?
- Which ligaments, cartilage, labrum, capsule, or other structures help stabilize the joint?
This framework keeps you from treating every painful spot as a tendon problem. It also gives you clearer language for a clinical conversation, especially if shoulder symptoms interfere with work at a desk, lifting, exercise, or a sport. Describing the tissue connection and the movement separately is more useful than using “shoulder tendon” as a label for every symptom.
The four rotator cuff tendons: the core anatomy map
The rotator cuff is a group of four tendons that connects its muscles to the humerus. The four rotator cuff tendons are the supraspinatus, infraspinatus, teres minor, and subscapularis tendons. Together, they form the central tendon map around the shoulder joint.
The names identify four related structures, but they do not tell you that one tendon is responsible for every movement or that pain in a particular area proves injury to one of them. The tendons blend at their insertion sites, so their anatomy is connected rather than divided into four completely separate zones.
Each of the four rotator cuff tendons attaches at the upper end of the humerus. That shared relationship gives you a broad location: the tendons run from rotator cuff muscles toward the upper arm bone at the shoulder. It is more accurate than treating the skin over the front, side, or back of the shoulder as a precise tendon map.
For orientation, keep the four names together:
- Supraspinatus: a rotator cuff tendon attached at the upper end of the humerus.
- Infraspinatus: a rotator cuff tendon attached at the upper end of the humerus.
- Teres minor: a rotator cuff tendon attached at the upper end of the humerus.
- Subscapularis: a rotator cuff tendon attached at the upper end of the humerus.
The general anatomy identifies their shared cuff group and humeral attachment. It does not allow you to diagnose a tear or irritation by matching one name to one symptom. A broad anatomy map should not be treated as four precise skin landmarks. The tendons blend at their insertion sites, so a symptom felt at the front, side, or back of the shoulder cannot by itself establish which tendon is involved. Use the four names to follow a clinician’s explanation of the cuff, then pair the observed location with the movement and functional change rather than treating location as proof.

How the rotator cuff supports shoulder movement and stability
The rotator cuff tendons attach to the upper end of the humerus and help center the humeral head in the glenoid so the deltoid can power the shoulder overhead. The deltoid is a larger muscle that contributes to overhead movement. The cuff’s role is therefore more than producing movement: it contributes to the positioning that lets a larger muscle move the arm overhead.
This relationship is why shoulder function is shared across tissues. A difficulty lifting your arm does not, by itself, identify which tendon, muscle, joint surface, or stabilizing structure is involved. It describes a movement problem that needs to be considered with the shoulder’s broader anatomy.
The supraspinatus and infraspinatus tendons contribute to shoulder stability and motion, and the rotator cuff tendons blend at their insertion sites. Those facts support a connected view of the cuff rather than a simple chart in which every symptom belongs to one isolated tendon.
You can use the movement itself as useful history without turning it into a diagnosis. Note whether the problem appears during overhead reaching, rotation, pushing, pulling, or another task, then describe what you can and cannot do. The four rotator cuff tendons—supraspinatus, infraspinatus, teres minor, and subscapularis—work together to help center the humeral head for overhead movement; the supraspinatus and infraspinatus contribute to motion and stability, and the long head of the biceps is a separate shoulder tendon. This gives you a two-level map: the cuff has a shared role in centering the humeral head and supporting overhead movement, while the supraspinatus and infraspinatus are specifically described as contributing to motion and stability. Therefore, describe what movement is limited without turning that movement into a tendon label.
The long-head biceps tendon belongs to the broader shoulder tendon map
The long head of the biceps is a tendon in the shoulder region, separate from the four rotator cuff tendons. That distinction matters because the phrase “shoulder tendon” covers more than the rotator cuff. A shoulder concern may involve the cuff group, the long-head biceps tendon, or another structure in the joint’s surrounding system.
Naming additional shoulder tendons does not establish that any particular one is causing your symptoms.
Use the long-head biceps tendon as a reminder to keep your description precise. You can tell a clinician whether discomfort feels more prominent at the front, side, or back of the shoulder, but surface location is not a diagnosis. A symptom may be near one structure while the relevant assessment needs to consider several structures together.
That broader map is especially useful if your shoulder pain followed an activity change, repetitive training, a fall, or another event. Describe the context and the movement that brings on the symptom rather than deciding in advance that the rotator cuff or biceps tendon is responsible.

Shoulder mobility depends on coordinated support from several structures
If you are trying to make sense of shoulder symptoms while working, training, or returning to an activity in Palo Alto or elsewhere in the Bay Area, separate the movement you are attempting from the structure you suspect. Record the movement and its effect. Leave the tissue identification to an assessment that considers the joint as a whole. The shoulder’s movement vocabulary is broader than simply “lifting the arm”: it can flex and extend, abduct and adduct, circumduct, and rotate medially and laterally. That range comes with relative instability, and the joint is prone to subluxation and dislocation. For a reader tracking symptoms, this makes the movement itself useful context: record whether the difficulty appears during reaching forward, moving away from the body, rotating, or making a circular motion. That record describes the demand placed on a highly mobile joint without claiming that one movement identifies one injured tendon.
Shoulder tendon problems may cause overlapping symptom patterns
Shoulder symptoms can overlap because tendon problems are closely related to shoulder function and stability. If you notice pain, weakness, or reduced function with shoulder use, those details are worth recording, but they do not identify a specific tendon. The same general experience can sit within a problem involving muscles, bursae, ligaments, nerves, bones, or more than one structure.
For example, pain while reaching overhead may tell you that a movement is difficult. It does not tell you whether the relevant issue is the supraspinatus, another rotator cuff tendon, the long-head biceps tendon, a bursa, a ligament, or a non-tendon structure. The symptom is a starting point for questions, not an anatomical label.
Shoulder history becomes more useful when you describe the full pattern:
- Where you notice the symptom and whether the location changes.
- Which movements or activities bring it on.
- Whether weakness or reduced function limits a task.
- How long the problem has been present and whether it followed an injury.
This information does not replace an examination. It gives a clinician a clearer account of how the shoulder is behaving so the tendon question can be considered alongside the rest of the joint.
Why shoulder symptoms cannot confirm which structure is affected
Shoulder symptoms cannot confirm which structure is affected because tendons and muscles function within a joint that also contains bursae, ligaments, nerves, bones, cartilage, the labrum, and the capsule. A painful movement may involve coordination among several of those structures. Even a symptom that feels very specific can have more than one possible anatomical explanation.
A better question than “Which tendon do I have?” is “Which structures need to be assessed, and what findings would distinguish them?” That question keeps the conversation open until the history, examination, and any appropriate testing are considered together.
Imaging may contribute to the assessment, but the choice of test belongs within a clinical assessment rather than a self-directed diagnosis.
Bring any prior imaging information to the appointment and ask what clinical question the next test is meant to answer. An image is most useful when it is interpreted alongside your symptoms, function, examination findings, and the other structures that may contribute to shoulder pain. Imaging choices are not interchangeable: X-rays show the bones that make up the shoulder, while MRI and ultrasound provide better pictures of soft tissues, and MRI may help identify injuries to surrounding ligaments and tendons. The practical question to bring to a clinician is what structure or clinical question a proposed study is intended to clarify. That context can explain why a test is considered without turning the result into a self-directed diagnosis.
Questions and details to bring to a shoulder evaluation
A shoulder evaluation is easier to discuss when you bring a concise account of the problem and the questions you want answered. Use this checklist before an appointment:
- Location: Mark where you feel the symptom and whether it spreads or changes.
- Duration: Note when it began, whether it is constant or intermittent, and whether it is improving, stable, or worsening.
- Triggers: List the movements, work tasks, exercise, sleep positions, or sports that make it easier or harder to use the shoulder.
- Function: Describe any task you avoid or cannot complete, including reaching, dressing, lifting, or overhead activity.
- Injury context: Explain whether the problem followed a fall, a sudden load, repetitive use, or no clear event.
- Previous information: Bring prior MRI or X-ray imaging and reports when available.
- Questions: Ask which structures need assessment and whether ultrasound, MRI, or another approach would address the clinical question.
The purpose of these details is to support a focused conversation, not to produce your own tendon diagnosis. Ask how the findings fit together across tendons, muscles, bursae, ligaments, nerves, and bones. Ask what the examination shows and what a proposed test is intended to clarify.
This approach works whether your shoulder problem affects a Palo Alto commute, computer work, weekend cycling, swimming, climbing, racquet sports, or another activity. The activity gives useful context because it shows what the shoulder needs to do; it does not identify the tissue involved. If you have more than one affected activity, list them separately so the change in function is easier to describe.
Use persistent or concerning symptoms as a reason to seek assessment
Persistent, severe, or concerning shoulder symptoms warrant professional assessment rather than continued self-diagnosis from an anatomy diagram. Anatomy can help you describe the problem, but it cannot determine whether you have a tendon injury, identify its severity, or establish which option is suitable for you. A qualified clinician decides individual suitability after considering your history, examination, and relevant findings.
Before an assessment, note where symptoms occur, which movements affect them, how long they have lasted, and which shoulder tasks are difficult. Those details can turn a confusing anatomy question into a more focused assessment.
What should I ask about during a shoulder tendon evaluation?
What is the most commonly injured tendon in the shoulder?
A shoulder anatomy overview cannot identify one tendon as the most commonly injured. Shoulder problems may involve a rotator cuff tendon, the long-head biceps tendon, or nearby structures, and symptoms alone cannot identify the affected tissue. An examination is needed to determine what should be assessed.
How can you tell whether shoulder pain involves a tendon or a ligament?
You generally cannot tell reliably from pain location or a single movement. Tendons connect muscles to bones, while ligaments connect bones to bones, but both work alongside the labrum, capsule, cartilage, bursae, nerves, and muscles. A clinician may use your history, physical examination, and—when appropriate—ultrasound or MRI to clarify the possibilities.
What should you do if shoulder tendon symptoms persist or limit activity?
Arrange a professional evaluation rather than trying to identify the injured tendon from an anatomy diagram. Record when symptoms began, which movements or activities bring them on, whether you have weakness or reduced function, and whether an injury preceded them. Bring prior MRI or X-ray reports if available, and describe the tasks you can no longer perform comfortably.
Next step
Have a question for RegenCore?
Concierge regenerative & orthobiologic orthopedics in San Francisco and Palo Alto. Research-backed, non-surgical treatment — PRP, bone marrow concentrate (BMAC), stem cell therapy, shockwave, EMTT and spinal disc care — to help the body heal itself.
Get in touch