
knee surgery arthroscopic
Knee Arthroscopy: What the Procedure Does and What Evidence Can Tell You
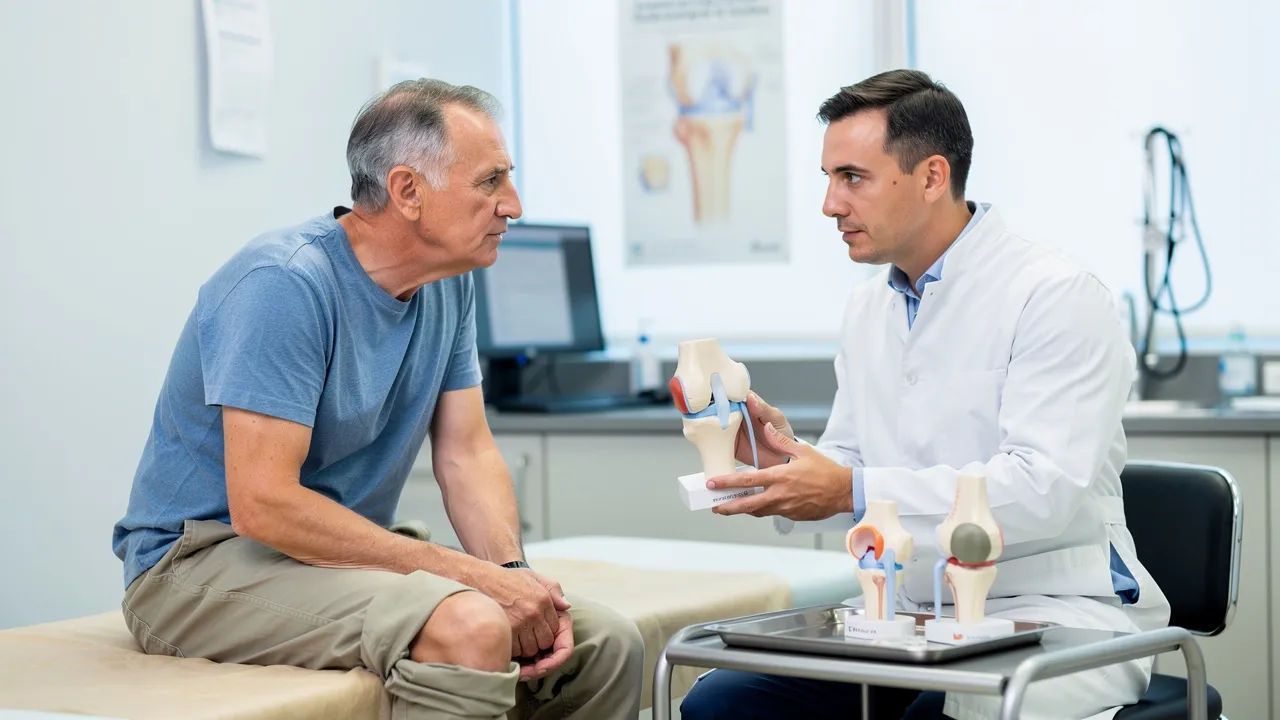
Arthroscopy is a technique, not a single treatment
Knee arthroscopy does not name one uniform treatment. The term refers to a surgical technique that can be used for different procedures, so the practical question is what work is proposed and which knee problem it is meant to address. A procedure intended to trim meniscus tissue is not interchangeable with one that sutures a tear, and evidence about one should not automatically be treated as evidence about the other.
A British Journal of Sports Medicine blog passage says the literature did not support traditional arthroscopic procedures for degenerative knee disease, including joint lavage, washout of material inside the joint, and partial meniscectomy. The same passage distinguishes those procedures from arthroscopy as a whole. That distinction matters if you are discussing surgery: ask for the exact procedure and diagnosis, rather than relying on the word “arthroscopy” to tell you what the operation is expected to do.
What arthroscopy is intended to do and what to clarify about the procedure
Knee arthroscopy can involve washing out the joint, removing material from inside it, trimming damaged meniscus tissue, or suturing some meniscus tears.
Your description of the proposed procedure should be concrete enough that you can explain it back in your own words. You might ask: “What is the name of the specific procedure?” “What tissue or finding is it intended to address?” “What will the surgeon do to that tissue?” and “What change are you hoping that work will make for me?” If the answer remains only “arthroscopy,” ask what the term means for the actual plan being discussed.
The purpose also deserves a separate question from the mechanics. Ask what benefit is expected for your particular knee problem, what would count as a meaningful change in pain or function, and how you will know whether the intended goal has been met. A clear explanation connects the diagnosis, the proposed action, and the outcome you care about, such as returning to a usual activity. It does not assume that the same procedure has the same purpose for every knee.
Trimming damaged meniscus tissue and repairing a tear are different
Meniscus trimming and meniscus repair involve different work and have a supported difference in recovery expectations. AAOS OrthoInfo describes partial meniscectomy as trimming away damaged meniscus tissue. It says some tears can be repaired by suturing the torn pieces together, and that the possibility of successful repair depends on the tear type and the overall condition of the injured meniscus.
| Procedure | Work described | Recovery comparison |
|---|---|---|
| Partial meniscectomy | Damaged meniscus tissue is trimmed away. | Serves as the comparison for repair recovery. |
| Meniscus repair | Torn pieces are sutured together when repair is an option. | Recovery takes longer than after meniscectomy because the meniscus must heal back together. |
That recovery comparison is a direction, not a personal timetable. AAOS OrthoInfo explains why repair can take longer: the meniscus has to heal back together. The source also makes repair success conditional on the tear type and the overall condition of the injured meniscus. Ask which of those features matters in your case, what supports the proposed choice between trimming and repair, and what recovery expectations follow from that specific plan. AAOS OrthoInfo also says partial meniscectomy typically allows immediate weight bearing and full range of motion soon after surgery. That general description is not a personal clearance; ask the treating clinician what activity is permitted after the specific procedure.
A useful conversation separates three questions that can otherwise blur together: What is the tear? What work is proposed? What recovery does that work involve? If you have heard only that a tear is present, ask whether the plan is to remove damaged tissue, bring torn pieces together with sutures, or consider another course. Then ask why that approach fits the tear and the condition of the meniscus, and what details could change the choice. AAOS OrthoInfo also notes that when the meniscus is largely gone, ongoing pain may occur and osteoarthritis may develop. It describes meniscus transplant—replacement of the damaged meniscus with donor tissue matched for size—as a possible alternative for younger, active people who do not want partial or total knee replacement. This is a specific option for a defined group, not a general substitute for arthroscopy. If it comes up, ask what finding makes it relevant and how its purpose compares with the procedure being discussed.
Evidence on degenerative knee disease applies to specific procedures
Evidence discussed for degenerative knee disease needs to be tied to the procedure it concerns. A British Journal of Sports Medicine blog passage says the literature did not support traditional procedures such as joint lavage, washout of material inside the joint, or partial meniscectomy for degenerative knee disease. It does not present that point as a blanket verdict on every procedure performed arthroscopically. If your diagnosis includes degeneration, ask whether the evidence being discussed concerns the same procedure and the same kind of knee problem as yours.
The same blog passage describes a proposed procedure called arthroscopic cartilage regeneration facilitating procedure and reports that Lyu and colleagues found about 85% of patients were satisfied; among patients with grade IV knee osteoarthritis, reported satisfaction was 59%. These are reported satisfaction figures for that particular procedure and those described groups. They are not a prediction of your result, and they do not turn one procedure’s findings into evidence for all forms of knee arthroscopy.
When a result is presented to you, ask what procedure produced it, what condition was being treated, and which group the result describes. A figure can sound precise while still answering a narrower question than the one you need answered. For example, a reported satisfaction percentage is not automatically a measure of pain relief, restored activity, or the likelihood that you will avoid another treatment. Ask what the stated measure means before using it to weigh a decision.

A study’s patient group and comparison shape what its findings mean
A New England Journal of Medicine study passage describes a selected group with a degenerative tear of the medial meniscus and no osteoarthritis. Investigators considered those participants likely to benefit from arthroscopic partial meniscectomy, and highly experienced surgeons performed the operations. Those details tell you who was studied; they do not make that group a stand-in for every person with knee pain, a meniscus tear, or arthritis.
The study used a sham-surgery control, which the passage says helped distinguish a treatment effect from nonspecific, or placebo, effects. That comparison is relevant when you hear a claim about what surgery itself accomplished. Ask whether a finding comes from a comparison designed to separate the procedure’s effects from other influences, and whether the people studied resemble you in the ways that matter to the decision.
Your diagnosis and the study population are separate parts of the question. A study of a degenerative medial meniscus tear without osteoarthritis does not, by its participant description alone, settle a question about a different tear pattern or a knee with osteoarthritis. Likewise, the fact that investigators expected a group to benefit explains their selection; it does not establish that you share the same relevant features. Keep the population, the operation, and the outcome measure together when you discuss a study.
Discuss expected benefits, limitations, risks, and recovery for your diagnosis
AAOS says its clinical practice guideline is not a fixed protocol and that care should reflect a clinician’s independent medical judgment in light of your specific circumstances. That principle is especially useful when a general statement about a procedure seems to conflict with the details of your knee problem. Ask how the recommendation applies to your diagnosis and what features of your situation affect the proposed plan.
Expected benefit should be described in terms you can use to make a decision. Ask what symptom or limitation the procedure is intended to change, what amount of change is expected, and what uncertainty remains about reaching that goal. You can also ask what the plan would mean if pain improves but a valued activity remains difficult, or if the result falls short of the intended change. These questions make the expected benefit specific without treating it as a promise.
Risks require a procedure-specific discussion rather than a generic list applied to every operation. Ask which risks are material for the procedure being proposed, how your health and knee findings affect that discussion, and what would change the plan. Ask what symptoms after the procedure should prompt you to contact the treating team and whom you should contact. Those answers should come from the clinician familiar with the proposed operation and your circumstances.
Recovery is also part of the treatment decision, not an afterthought. Ask for expected milestones for the activities that matter to you, such as walking, work, daily tasks, hiking, or sport, and ask how those expectations differ for the exact procedure under discussion. If the plan involves meniscus repair rather than trimming, include the supported comparison that repair takes longer because the meniscus must heal back together. Ask what could alter the recovery plan and how progress will be assessed.
Questions that make a discussion about arthroscopy more specific
A focused list of questions can help you leave the conversation with a clearer account of the diagnosis, proposed procedure, and decision. Choose the questions that match what you still need to understand:
- Diagnosis: “What specific knee problem are you treating, and what findings support that diagnosis?”
- Procedure: “What exactly will be done during the arthroscopy, and what tissue or finding is that work meant to address?”
- Meniscus tear: “Is the proposed plan to trim damaged tissue or repair the tear? How do the tear type and the overall condition of the meniscus affect that choice?”
- Evidence: “Does the evidence you are using concern this procedure and a patient group similar to mine? What outcome was measured?”
- Expected benefit: “What change in pain or activity do you expect, and what uncertainty remains?”
- Alternatives: “What other reasonable paths can I discuss, and what would I gain or give up with each?”
- Risks: “Which risks matter for this specific procedure and my circumstances? What symptoms should prompt me to contact the treating team?”
- Recovery: “What milestones should I expect for my daily activities and the activity I most want to return to? What factors could change that timeline?”
Your own priorities can make the answers more useful. Before the discussion, note which activities you most want to regain, what symptoms are limiting them, and what recovery demands you need to plan around. Bring the wording of the proposed procedure and the diagnosis you were given, if you have them. If an answer feels broad, ask for the detail that connects it to your knee: the finding, the procedure, the expected change, or the recovery milestone.
Use an evaluation to clarify the knee problem and next discussion
A clear next discussion starts with your knee problem and the exact procedure being considered. A qualified clinician must determine whether arthroscopy is appropriate for your diagnosis and circumstances.
Practical questions about knee arthroscopy
What does “knee surgery arthroscopic” mean?
It means a procedure is performed using arthroscopy, but it does not identify the specific treatment. Ask what work is planned—such as trimming damaged meniscus tissue or suturing a tear—and what knee finding it is intended to address.
Does knee arthroscopy treat osteoarthritis?
It depends on the procedure and the reason it is being proposed. The article notes that the literature discussed did not support traditional procedures such as joint lavage, washout, or partial meniscectomy for degenerative knee disease; that is not a blanket verdict on every arthroscopic procedure. Ask how the evidence applies to your diagnosis and the exact procedure under consideration.
How does meniscus repair recovery differ from meniscus trimming?
Recovery after repair takes longer than after partial meniscectomy because the meniscus must heal back together. The appropriate approach and your recovery expectations depend on the tear type and the condition of the meniscus, so ask your clinician about the plan for your specific tear.
What should I ask before deciding whether to have knee arthroscopy?
Ask what diagnosis and findings support the recommendation, what the surgeon will do, and what change in pain or activity is expected. Also discuss alternatives, procedure-specific risks, remaining uncertainty, and recovery milestones—including what symptoms after surgery should prompt you to contact the treating team.
Next step
Have a question for RegenCore?
Concierge regenerative & orthobiologic orthopedics in San Francisco and Palo Alto. Research-backed, non-surgical treatment — PRP, bone marrow concentrate (BMAC), stem cell therapy, shockwave, EMTT and spinal disc care — to help the body heal itself.
Get in touch