
neer test shoulder
Neer Test Shoulder: What the Finding Means and What Comes Next
What the Neer test can—and cannot—tell you
The test can add information about how your shoulder responds during the examination, but it cannot identify the exact cause of pain on its own.
Shoulder impingement involves the rotator cuff tendons or the bursa becoming pinched between the humerus and the acromion. That problem may be associated with pain, weakness, or difficulty reaching overhead or behind your back. Similar symptoms can occur with other shoulder conditions, so a test finding needs to be placed beside your history, strength, movement, and other examination findings.
The term can sound more definitive than it is. A test name describes a clinical maneuver; it does not automatically name the structure causing your pain or determine which treatment should follow.
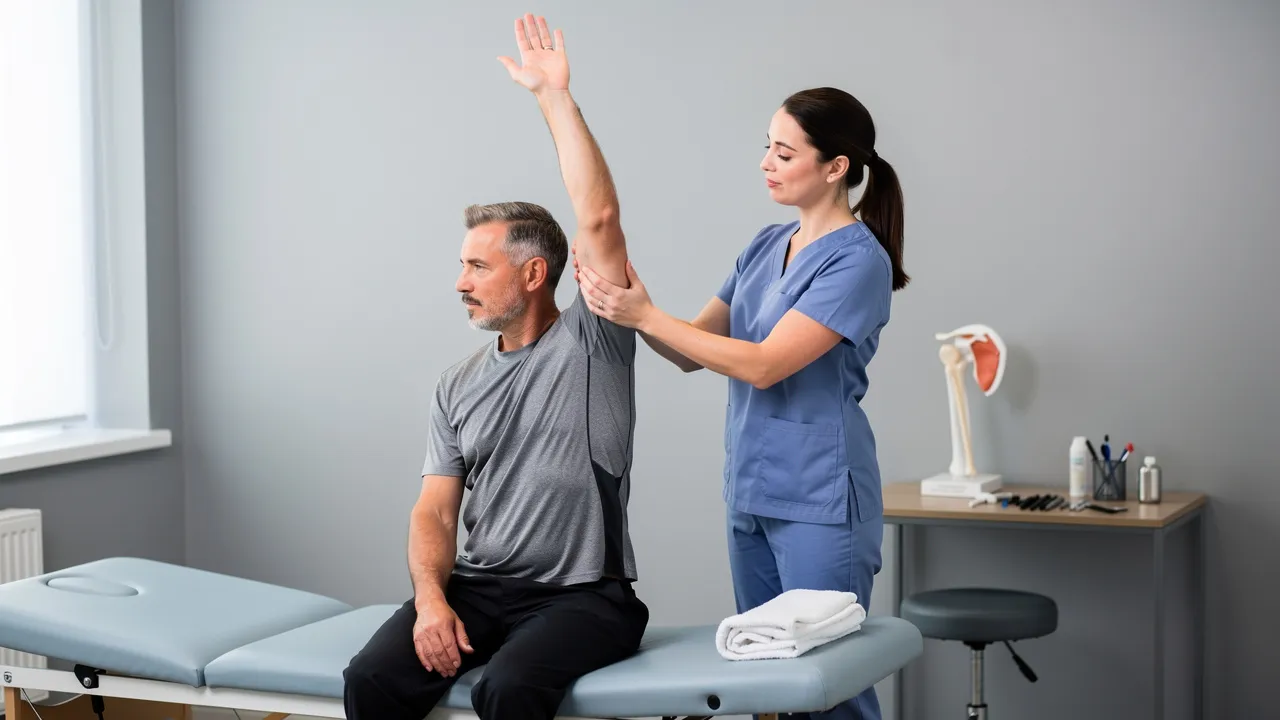
During a clinician-led shoulder movement, the Neer maneuver observes whether the movement reproduces the patient’s familiar pain; the response is interpreted alongside the history and other examination findings. Shoulder examinations can include both strength tests and provocative tests, and clinicians assess their diagnostic usefulness with measures such as sensitivity, specificity, and likelihood ratios. Those measures describe how much a test result changes clinical confidence; they do not turn one maneuver into a complete explanation for your pain.
If you have seen the term in a clinical note or online, the next useful question is not whether the test has named your injury. Ask what the finding means alongside your symptoms and what further evaluation, if any, fits your circumstances. That approach keeps the result in its proper role: one piece of a broader shoulder assessment.
Why clinicians use a provocative shoulder test
Shoulder examinations use provocative tests to add information when a particular movement or position brings on familiar symptoms. They are used alongside strength testing and the rest of the physical examination rather than as isolated yes-or-no answers.
A clinician may compare the painful shoulder with the opposite side, assess strength, and consider which movements reproduce your symptoms. The purpose is to build a pattern. A provocative result matters most when it agrees with the history and with other findings that point in the same direction.
This is why the same test result can lead to different discussions for different people. Your age, activity demands, injury history, pain pattern, movement, strength, and prior findings all affect how much weight a clinician gives the result.
Shoulder test diagnostic usefulness depends on more than whether a maneuver causes pain. Sensitivity, specificity, and likelihood ratios are used to describe how examination findings relate to the presence or absence of a condition, while clinical testing for different causes of rotator cuff-related shoulder pain has only moderate diagnostic value.
That distinction matters if you are active in Palo Alto, San Francisco, or elsewhere in the Bay Area and want to return to work, training, or sport. Pain during a maneuver deserves attention, but it should not decide your diagnosis, treatment, or activity plan by itself.
A useful appointment therefore focuses on the whole problem. The clinician can discuss what the finding adds, what questions remain unanswered, and whether another part of the evaluation should receive more attention.
One way to understand that approach is to separate a test’s result from the confidence attached to it. Sensitivity describes how often a test is positive among people who have the condition being assessed; specificity describes how often it is negative among people who do not. Likelihood ratios bring those ideas together to describe how much a result changes the probability of a condition. These are measures of diagnostic usefulness, not labels for the patient’s shoulder. They help a clinician judge how much weight to give the finding, especially when it does not agree with the history or with other examination findings.
For a reader, the practical implication is that a “positive” or “negative” result is an incomplete summary. The more useful question is what the result contributes to the working explanation and what information is still missing. That is why a clinician may record the response but continue with strength, movement, history, and, when appropriate, imaging. It also explains why repeating the same maneuver does not necessarily produce a clearer answer: a repeated label is not a substitute for information about the cause of pain.
How to interpret a shoulder test result
A positive test does not confidently prove subacromial bursitis, rotator cuff tendinopathy, or a rotator cuff tear. Those conditions can produce overlapping symptoms, and shoulder impingement itself may be associated with pain, weakness, or difficulty reaching overhead or behind the back.
Use the finding as a prompt to describe your pain precisely. Tell the clinician where it starts, which movements bring it on, whether weakness limits you, and how long the problem has been present. Those details help separate a suggestive examination response from a conclusion about an injury.
A positive result also does not automatically mean that you need an injection, a procedure, surgery, or a particular exercise program. The next decision depends on the broader assessment and on the problem that the clinician is trying to clarify.
Shoulder pain has more than one possible source
Chronic shoulder pain can result from several conditions, including rotator cuff disorders, adhesive capsulitis, shoulder instability, and shoulder arthritis. Shoulder pain is considered chronic when it has been present for longer than six months.
These conditions do not all affect the shoulder in the same way. Your pain may be related to a tendon problem, restricted motion, instability, or joint changes, and a provocative finding cannot separate every possibility. The label attached to one test should not replace an assessment of the broader pattern.
That broader pattern can include differences in motion and history that a provocative response does not describe. For example, adhesive capsulitis may present with diffuse shoulder pain and restricted passive range of motion. Shoulder instability may be associated with a history of dislocation or subluxation, while glenohumeral arthritis may present with gradual pain and loss of motion. These examples do not allow a reader to identify a condition from symptoms alone. They show why the clinician asks about both what hurts and what the shoulder can or cannot do during assessment.
The same finding can therefore sit inside different clinical questions. Is the main issue pain with use, loss of motion, weakness, or a history of the joint giving way? The answer does not make a diagnosis by itself, but it helps determine which parts of the examination and any later investigation deserve attention. A Neer finding is one response during assessment; it does not replace this broader comparison or establish which condition is present.
The time course also matters. Pain that began after a particular injury raises different questions from pain that developed gradually with repeated activity, even when both situations produce discomfort during an examination maneuver.
Rotator cuff disorders include tendinopathy, partial tears, and complete tears. Those are different problems even though they may share pain with reaching or other shoulder use.
The distinction matters because the next evaluation depends on the full clinical picture. Describe whether you notice weakness, loss of motion, instability, or pain during particular activities. Do not use a positive or negative Neer finding to choose exercises, injections, surgery, or another treatment without a broader professional assessment.
A test result cannot tell you which of these conditions is present by itself. It must be considered with the history, examination, and any imaging that is appropriate to the clinical question.
How clinicians build a more reliable picture
A complete shoulder assessment combines your symptom history, a clinical examination, and radiological investigation when appropriate rather than relying on one test. For rotator cuff-related shoulder pain, determining the cause should involve those sources of information together.
Your history gives the clinician a timeline and a description of what limits you. The examination adds observations about pain, movement, and strength. Imaging may answer questions that a physical maneuver cannot. Each part contributes a different kind of information.
This approach also helps keep the discussion focused. Instead of asking only whether the Neer test was positive, you can ask what explanation best fits the complete pattern and what information would change that explanation.
The shoulder assessment sequence may vary with your circumstances. A practical discussion can cover:
- When the pain began and whether an injury or repetitive activity preceded it.
- Which movements, work tasks, training sessions, or sleep positions bring on symptoms.
- Whether weakness, stiffness, instability, or loss of function accompanies the pain.
- What the physical examination shows beyond the Neer finding.
- Whether imaging or another diagnostic approach would add useful information.
Clinical guidance is not a fixed protocol. Different diagnostic or treatment approaches may be appropriate for different circumstances, and the plan should reflect independent clinical judgment rather than a preset response to one test.
Bring questions about the reasoning, not only the result. Understanding what the clinician is assessing can make it easier to decide what information to provide and what follow-up to discuss.

When imaging may add useful information
Shoulder imaging may add information when the clinical assessment raises a question that a physical examination cannot answer. MRI and ultrasound can provide better images of shoulder soft tissues than X-rays, and MRI may help identify injuries to the ligaments and tendons surrounding the shoulder joint.
That does not mean every shoulder problem requires an MRI or ultrasound. The appropriate study depends on what the clinician is trying to evaluate, what has already been learned from your history and examination, and your specific circumstances.
Imaging should therefore follow a clinical question. The goal is not to collect a scan simply because a test was positive, but to determine whether a particular study could add information that changes the assessment.
The clinician decides whether that distinction is relevant to your presentation.
Bring prior reports and images if you have them. Reviewing existing information can be part of a broader evaluation, but it does not make a new test automatically necessary or establish a treatment choice by itself.
Ask what the proposed imaging is intended to clarify and how the result would affect the next discussion. That keeps the scan connected to your symptoms and examination rather than treating it as a substitute for either one.
When to arrange a professional shoulder evaluation
Shoulder pain lasting longer than six months is considered chronic, but you do not need to wait six months to discuss pain that is limiting your work, sleep, training, or daily activities.
Arrange an evaluation if the problem continues, your shoulder function is changing, or you are unsure what a test result means. The purpose is to identify the questions that need answering and to match the assessment with your symptoms, examination, and circumstances.
A professional discussion is also reasonable when you have received a test result without a clear explanation of what it means. The result can be reviewed alongside your history instead of becoming the sole basis for a decision.
A shoulder appointment is easier to use when you bring a short, concrete history:
- Note when the pain started and whether it followed an injury, repeated overhead activity, or another change.
- Describe the location, intensity, and timing of the pain in your own words.
- List movements or activities that are harder than before.
- Bring the wording of any Neer result and copies of prior imaging reports or images.
- Ask what the finding suggests, what it does not establish, and whether further evaluation is appropriate.
Clinical guidance should reflect your specific circumstances. A test result should support that discussion, not replace it.
You do not need to provide a perfect medical label. A clear account of what changed, what aggravates the shoulder, and what you can no longer do gives the clinician useful starting information.

Discussing non-surgical options after evaluation
Non-surgical shoulder care can be discussed after the source of shoulder pain and your individual circumstances have been assessed. A Neer finding alone cannot establish which treatment is appropriate, whether you are eligible for it, or what result you should expect.
Evidence for multimodal physical therapy in subacromial shoulder pain is variable and includes low-level evidence, with its clinical significance remaining unclear. That finding supports a careful conversation about options; it does not support choosing a particular therapy from a single examination result.
The same principle applies to other non-surgical choices. The label attached to the test should not be treated as a treatment prescription.
Questions for a shoulder treatment discussion can include:
- What working explanation best fits my history and examination?
- What additional information would change the plan?
- What are the non-surgical choices for this situation?
- What limitations, trade-offs, or follow-up would each choice involve?
- How should I judge whether the plan is helping or needs reassessment?
Clinical guidance is not a fixed protocol, and different patients may need different diagnostic or treatment approaches. The decision should follow the full assessment rather than the label of a positive or negative test.
If you are considering care in Palo Alto or the wider Bay Area, bring the same questions to the evaluation. The location does not change the basic need to connect any proposed option to your symptoms, findings, and circumstances.
Before discussing a non-surgical option, it can help to clarify four separate points. First, what problem is the clinician trying to address: pain, restricted movement, weakness, or another finding? Second, what evidence from the history and examination supports that working explanation, and what remains uncertain? Third, what role would the proposed option have in the plan, including what other approaches might be considered? Fourth, how would you and the clinician review progress and decide whether the plan needs reassessment? These questions do not select treatment for you. They make the decision criteria visible and keep the conversation tied to the reason for evaluation.
This distinction is particularly important when a test result feels definitive. A procedure or therapy should not be chosen merely because its name appears to match a shoulder label. The clinician still needs to weigh the complete presentation, the limits of the available evidence, and the fact that clinical guidance is not a fixed protocol. If the explanation changes after further examination or imaging, the discussion may change as well. That is not a failure of the first conversation; it is the purpose of evaluating uncertainty before committing to a plan.
How RegenCore Method approaches an evaluation
At RegenCore Method, our evaluations include a thorough history, a hands-on orthopedic examination, diagnostic ultrasound, review of prior MRI or X-ray imaging, and a personalized treatment and recovery plan. That structure reflects the same practical principle discussed throughout this guide: a shoulder test is one piece of a broader evaluation.
At RegenCore Method, we combine examination, imaging review, and diagnostic procedures to confirm the source of pain. The purpose is to discuss the findings in context rather than treat a Neer response as a stand-alone answer.
Our process is designed to give the evaluation a defined sequence: understand the symptoms, examine the shoulder, consider available imaging, and discuss a plan that reflects the findings. The plan is made after assessment rather than selected from the test name alone.
At RegenCore Method, we bring together your symptom history, examination findings, prior imaging, and questions about next steps for a shoulder evaluation in Palo Alto or the wider Bay Area. We can discuss non-surgical possibilities only after the evaluation has considered the source of your pain and your circumstances.
A personalized treatment and recovery plan is part of our evaluation process. It is a plan for discussion after assessment, not a promise that one test result will determine a therapy or outcome.
You can use the appointment to explain what the finding means in the context of your activities, work, training, or daily function. The resulting conversation should address the broader shoulder problem rather than treat a positive or negative maneuver as a final answer.
Use the Neer finding to guide your next conversation
Bring the result together with the details that make it meaningful: when your pain began, what activities aggravate it, what function has changed, and whether you have prior imaging. A qualified healthcare professional must decide how those findings fit your circumstances and which next step is appropriate.
If your shoulder pain persists or significantly affects your use of the arm, arrange a professional assessment instead of forcefully repeating the maneuver or choosing treatment from the result.
For persistent or significant shoulder pain in the Palo Alto or Bay Area context, RegenCore Method offers an evaluation that includes history, a hands-on orthopedic examination, diagnostic ultrasound, imaging review, and a personalized treatment and recovery plan. A qualified professional decides how those findings fit your individual circumstances.
Questions readers often have about the Neer test
Can a positive Neer test diagnose a rotator cuff tear?
No. A positive finding cannot identify a rotator cuff tear, tendinopathy, bursitis, or another specific condition by itself. Interpretation depends on your history, examination, and any imaging that is appropriate.
What should happen after a Neer test for shoulder pain?
Bring the result to a qualified clinician with information about when the pain began, which movements aggravate it, changes in strength or motion, and how it affects daily activities, work, or sport.
Does a negative Neer finding mean the shoulder is normal?
No. A negative result cannot identify the cause of shoulder pain or establish that the shoulder is normal.
When might imaging be considered after a shoulder examination?
Imaging may be considered when the history and physical examination leave a question that a scan could clarify. The appropriate study depends on the clinical question and your circumstances.
Next step
Have a question for RegenCore?
Concierge regenerative & orthobiologic orthopedics in San Francisco and Palo Alto. Research-backed, non-surgical treatment — PRP, bone marrow concentrate (BMAC), stem cell therapy, shockwave, EMTT and spinal disc care — to help the body heal itself.
Get in touch