
shoulder region
What Is the Shoulder Region? A Clear Map of Its Anatomy and Symptoms
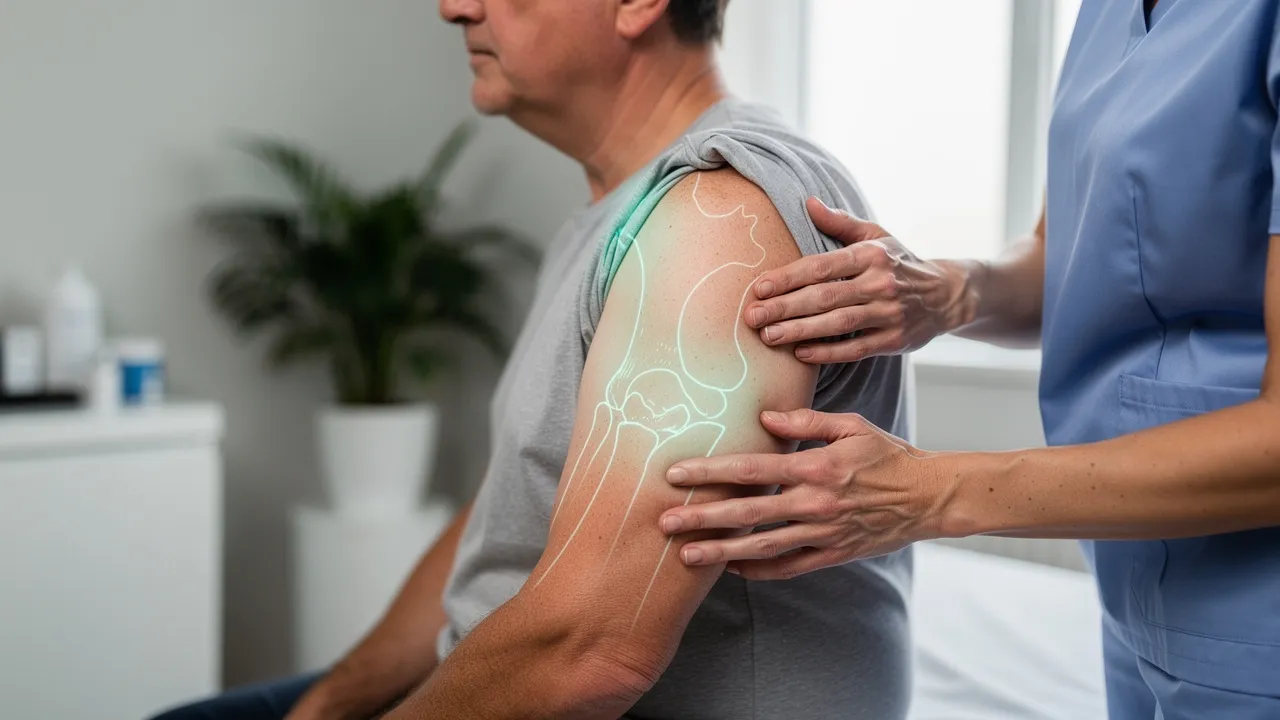
What “shoulder region” means
The shoulder region is a practical location term for the connected area where your trunk meets your upper limb. It does not name one single spot, one tissue, or a diagnosis.
The shoulder girdle links the trunk to the upper limb and has an important biomechanical role in daily activities. That connection explains why discomfort may be noticed while you reach, lift, rotate your arm, carry something, or move your shoulder blade. The place where you feel pain helps you describe the problem, but it does not identify the cause by itself.
A useful starting description uses ordinary location words:
- Front: near the collarbone or the front of the joint
- Top: where the collarbone meets the upper part of the shoulder blade
- Side: around the outer shoulder or the deeper ball-and-socket area
- Back: near the shoulder blade or the back of the joint
- Near the neck: close to the transition between the neck and shoulder
Then add what the symptom does. Note whether it stays in one place, changes with a particular movement, travels down your arm, or occurs with weakness, tingling, or numbness. Those details make the map more useful without turning it into a self-diagnosis.
Think of the area as a connected system rather than a single painful dot. The sections below move from the larger anatomical map to the joints, tissues, symptom patterns, and warning signs that can guide your next decision.
The shoulder region is a connected anatomical system
The shoulder girdle is a connected anatomical system made up of four joints and two bones rather than one isolated joint. The four joints are the glenohumeral, sternoclavicular, acromioclavicular, and scapulothoracic joints. The two named bones are the clavicle and scapula. Together, these structures form the framework commonly described as the shoulder area and connect the upper limb with the trunk.
The glenohumeral joint is the joint most people picture when they say “shoulder joint,” but it is only part of the larger map. The shoulder is structurally and functionally complex and includes bone, hyaline cartilage, labrum, ligaments, capsule, tendons, and muscles. A symptom felt near the outer shoulder may therefore sit over a different structure from a symptom felt on top of the collarbone or along the shoulder blade.
The four joints have different positions and relationships:
- Glenohumeral: the main ball-and-socket connection between the upper arm and shoulder blade
That flexibility supports many ordinary actions, but it also means that your description should include more than the position of the pain.
Use three questions to make the larger map clearer:
- Where do you feel the symptom: front, top, side, back, collarbone, shoulder blade, or near the neck?
- Which movement or activity changes it, if any?
- Does the symptom stay local, or does it travel into the arm?
These questions organize what you notice. They do not determine which structure is responsible.
Map the front, top, side, and back of the shoulder
The front, top, side, and back of the shoulder correspond to different landmarks within the same connected map. Describing the landmark nearest your symptom can make your account more precise, even though location alone cannot establish a diagnosis.
- Front and collarbone: The clavicle, or collarbone, forms part of the shoulder girdle. – Top of the shoulder: The acromioclavicular joint is where the acromion, part of the scapula or shoulder blade, meets the clavicle or collarbone. If you can point to the top of the shoulder, describe whether the symptom is near this meeting point or farther toward the arm.
- Side and deeper joint area: The glenohumeral joint is where the humeral head, or ball, meets the glenoid, or socket. You can describe discomfort here as deep, outer, or centered around the ball-and-socket area, without assuming which tissue is involved.
The shoulder girdle also includes the scapulothoracic joint, so a description along the blade belongs in the broader shoulder map even when the discomfort is not at the front of the joint.
This map gives you useful language for a clinical conversation. You might describe a symptom as “on top near the collarbone,” “deep at the outer shoulder,” or “along the shoulder blade.” You can then add whether it changes when you raise your arm, reach across your body, rotate your arm, or move your neck.
Location also has limits. A symptom near the back of the shoulder may be associated with a local shoulder structure, a nearby area, or a nerve-related pattern. The map helps you report what you feel; history and examination are needed to interpret it.
Before you describe the symptom, compare both sides visually and by location rather than trying to label a condition. Note the exact spot with one finger, then describe the size of the area: a small point, a broad patch, or a line that travels. That distinction can be more useful than saying only “my shoulder hurts.”

The tissues that support shoulder movement and stability
The tissues around the shoulder support movement, connection, and stability in different ways. The shoulder includes bone, hyaline cartilage, labrum, ligaments, a joint capsule, tendons, and muscles. Because these tissues sit close together, the same general location can be associated with more than one possible source of discomfort.
The rotator cuff connects the humerus to the scapula. It consists of the tendons of four muscles: the supraspinatus, infraspinatus, teres minor, and subscapularis. Those names describe the muscles whose tendons make up the cuff; you do not need to memorize them to describe your symptoms. It is enough to note the location, the movement that changes the symptom, and any change in strength or motion.
The glenohumeral socket, called the glenoid, is shallow and flat. The labrum deepens the socket, while the rotator cuff muscles help keep the humerus tightly in it. The glenohumeral joint is also one of the most flexible joints in the body, so mobility and stability depend on a coordinated system rather than on the ball-and-socket surfaces alone.
A tissue-oriented symptom map can include these observations:
- Is the discomfort close to the collarbone or on top of the shoulder?
- Does it feel deep at the ball-and-socket area or more superficial along the shoulder blade?
- Do you notice reduced motion, weakness, swelling, or a loose-feeling socket?
- Does a particular action change the discomfort, or does it continue without a clear movement link?
Those observations describe function and location. They do not tell you which tendon, ligament, cartilage surface, or other tissue is involved. Naming a structure requires more than matching a painful spot to an anatomy diagram.
What symptom location can—and cannot—tell you
Symptom location can help you describe a shoulder problem, but location alone cannot establish its cause. Shoulder pain can arise from overuse, wear and tear, or injury. Shoulder impingement involves pinching of soft tissues and can be associated with activity or damage that compresses tissue in the shoulder area.
A movement-related pattern may add useful detail. Note whether the discomfort appears while reaching, lifting, putting on clothing, turning your arm, or resting. These descriptions show how the symptom behaves, but they do not prove that a particular tendon, joint, or condition is responsible.
The timing of the symptom adds another layer. Record whether it began after a distinct event, followed repeated activity, or developed without a clear trigger. Then note whether it is improving, unchanged, recurring with the same activity, or becoming more limiting. A symptom that changes over time should be described as a pattern rather than reduced to its most noticeable location.
Your symptom account should also distinguish pain from changes in function. Weakness, reduced motion, swelling, a loose-feeling joint, or altered sensation may matter even when the pain itself is not severe. Conversely, pain intensity alone does not identify the structure involved.
A clinician’s diagnosis of a shoulder problem is based on history and examination. Your symptom description is useful because it gives the clinician a starting point, not because it replaces the assessment. Use location as one part of the account, alongside onset, movement, persistence, trauma, and associated sensations.
When discomfort may come from the neck or another nearby area
Pain near the shoulder can sometimes be associated with the neck or a nerve pathway rather than remaining a local shoulder symptom. Pain that radiates into the arm or shoulder area and varies in distribution can be associated with cervical radiculopathy. By contrast, pain from a local shoulder problem tends to remain localized and not travel or vary.
The pattern matters more than a single location label. You may notice pain near the shoulder blade, pain that extends down the arm, or a sensation that appears in different places at different times. Cervical nerve-root symptoms may also include tingling, weakness, or numbness in the shoulder or arm in addition to pain.
Describe the route of the symptom as carefully as its starting point:
- Where does it begin?
- Does it remain near the shoulder, or does it move down the arm?
- Does the distribution stay the same, or does it change from one episode to another?
- Do tingling, weakness, or numbness occur with the pain?
- Does moving your neck change the symptom, or is the change linked mainly to the arm and shoulder?
These features do not let you diagnose a neck condition on your own. They do give you a reason to describe the full route of the symptom instead of reporting only “shoulder pain.” Include the details when you arrange clinical assessment so the shoulder, neck, and nerve-related routes can be considered together.
Local shoulder symptoms and neck-related symptoms can overlap in everyday language. A traveling or changing pattern is therefore a reason to give a broader account, not a reason to select a diagnosis from a list. The location map helps you communicate; history and examination help interpret it.
Use a symptom map before deciding on assessment
A shoulder symptom map is a short record of location, movement, onset, associated sensations, trauma, and persistence. Use it to organize what you notice before deciding how promptly to seek assessment; do not use it to assign yourself a diagnosis.
Record these details in plain language:
- Location: Mark the front, top, side, back, collarbone, shoulder blade, or area near the neck. If the symptom travels, describe its route into the arm and whether the route changes.
- Onset: Note whether it began after a fall, accident, lifting event, repetitive activity, or without a clear event. Record whether it appeared suddenly or developed over time.
- Movement and function: Write down which actions change it and whether you can move your arm as usual. Compare comfortable movement with movement that is limited, painful, or difficult.
- Associated sensations: Note weakness, tingling, numbness, swelling, or a feeling that the socket is loose. A changed shape is also significant.
- Course: Record whether the symptom is easing, staying intense, returning with the same activity, or continuing without improvement.
- Context: Include work, exercise, sport, sleep position, or another activity only as a description of what preceded or changes the symptom, not as proof of its cause.
This account gives you a concrete way to describe the problem during a clinical conversation. It also helps separate a single location from the broader pattern around it. A clinician’s diagnosis is based on history and examination, so the map is preparation for that process rather than a substitute for it.
Use the map to make a practical distinction. If a symptom is continuing, becoming more limiting, or accompanied by weakness, numbness, reduced motion, swelling, instability, or trauma, arrange medical assessment. Sudden severe pain with inability or difficulty moving the arm, sometimes accompanied by a change in shape, can be associated with a dislocated shoulder, broken bone, or torn or ruptured tendon..
When shoulder-region symptoms should be assessed
Shoulder symptoms should be assessed when they are intense and ongoing or when they affect strength, sensation, movement, shape, stability, or the surrounding tissue. Arrange medical assessment for any of the following:
- Intense and ongoing shoulder pain
- Weakness in the arm
- Numbness in the arm or hand
- Reduced motion
- A misshaped shoulder joint
- Swelling
- A loose-feeling shoulder socket
- Shoulder trauma
These signs do not identify a particular diagnosis, but they change the value of waiting and watching. A symptom that continues, becomes more limiting, or follows trauma deserves a clearer explanation than location alone can provide.
Bring your symptom map to the assessment. Include where the discomfort began, whether it travels, which movements change it, and whether strength or motion has changed. If you have noticed swelling, a changed shape, instability, or altered sensation, write those details down even if they appeared after the pain began.
Persistence and function belong together. A symptom that remains intense, limits motion, reduces arm strength, or changes sensation should not be judged only by where it hurts. Describe the full pattern and arrange medical assessment.
When symptoms need immediate attention
Certain shoulder symptoms need immediate attention rather than routine monitoring. Seek immediate emergency orthopedic care for severe shoulder pain after a fall or accident, a visible deformity, loss of sensation in the arm, fever with shoulder swelling, or inability to move the shoulder.
These warning signs are different from a symptom that is simply located in the shoulder area. The combination of severe pain and an accident, a visible change in shape, loss of sensation, fever with swelling, or complete inability to move the shoulder changes the urgency of the situation.
If your symptoms fit one of these patterns, focus first on obtaining immediate care. The front, top, side, or back location can be described after you have addressed the urgent concern.
Use the shoulder-region map to choose your next step
A symptom map helps you communicate location, onset, movement, associated sensations, trauma, and persistence without assuming a diagnosis. Use the map to describe whether your symptoms are settling, continuing, becoming more limiting, or showing a warning sign that needs prompt attention.
A qualified clinician should determine what your symptoms mean and whether any individual treatment is suitable for you. Bring the map and describe the full pattern, including symptoms that reach the arm or occur with weakness, tingling, or numbness.
The anatomical map is useful because it turns “shoulder pain” into a more specific account: where the symptom starts, where it travels, what changes it, and how it affects movement. That information gives the next clinical conversation a clearer starting point.
What should you clarify before arranging a shoulder evaluation?
Is the shoulder region the same as the shoulder joint?
No.
Can pain near the shoulder come from the neck?
Yes. Pain associated with the neck or cervical nerves may radiate into the shoulder or arm and may occur with tingling, numbness, or weakness. A traveling or changing pattern does not establish the cause, so describe the symptom route and arrange an assessment if it persists or affects function.
When should shoulder-region symptoms be assessed urgently?
Seek immediate emergency orthopedic care for severe pain after a fall or accident, a visible deformity, loss of sensation in the arm, fever with shoulder swelling, or inability to move the shoulder. Intense ongoing pain, weakness, numbness, reduced motion, swelling, instability, or other trauma also warrant medical assessment even without those emergency features.
What details should I note before a shoulder evaluation?
Record the exact location, whether the symptom travels, how and when it began, movements or activities that change it, changes in strength or motion, and any swelling, instability, tingling, or numbness. This information helps a clinician interpret the pattern through history and examination rather than relying on location alone.
Next step
Have a question for RegenCore?
Concierge regenerative & orthobiologic orthopedics in San Francisco and Palo Alto. Research-backed, non-surgical treatment — PRP, bone marrow concentrate (BMAC), stem cell therapy, shockwave, EMTT and spinal disc care — to help the body heal itself.
Get in touch